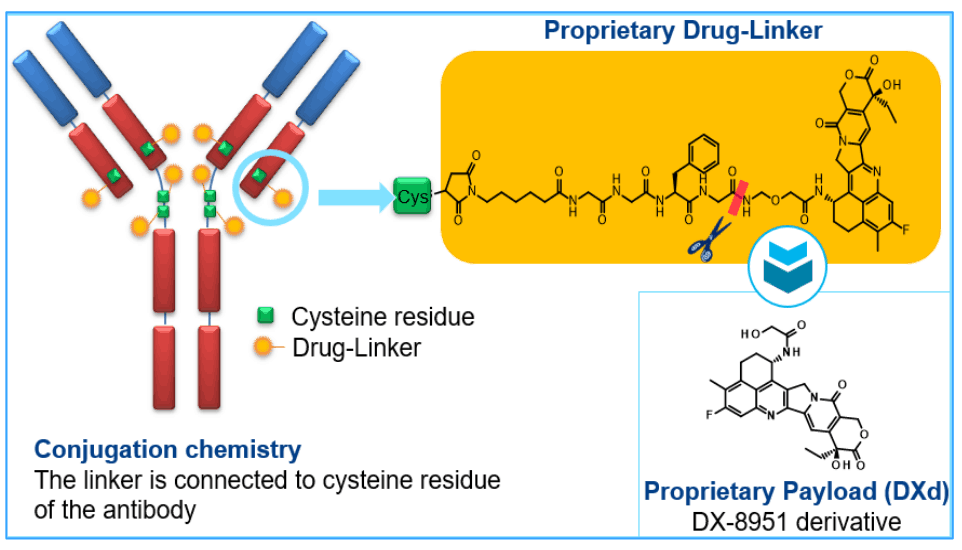
Trastuzumab deruxtecan
DrugWikipedia
174
MENTIONS
26
EPISODES
22
PODCASTS
Search complete. 174 mentions across 26 episodes found for "Trastuzumab deruxtecan".
Nov 3, 2026

Kohei ShitaraGUEST
I'm coming at, uh, ESMO twenty twenty-six.
Kohei ShitaraGUEST
In this ESMO meeting, we have presented the result from, uh, our investigator-initiated trial of a neoadjuvant, uh, T-DXd, capecitabine, and durvalumab combination for locally advanced HER2-positive gastroesophageal adenocarcinoma.
Kohei ShitaraGUEST
T-DXd is a anti-HER2 ADC, which already showed a survival benefit in gastric cancer at second line or later line and now already becomes a standard of care of this population.
Kohei ShitaraGUEST
Since T-DXd showed activity in combination with, uh, first-line capecitabine as well as anti-PD-1 in front-line setting, and the currently phase three study is ongoing, we intended to test this, uh, combination in perioperative setting.
Kohei ShitaraGUEST
Previously, we also conducted a T-DXd monotherapy as a neoadjuvant, uh, treat-treatment, and it showed five percent complete pathological response.
Kohei ShitaraGUEST
So it showed activity but not so enough.
Kohei ShitaraGUEST
So we have conducted this cohort.
Kohei ShitaraGUEST
Some degree of GI toxicity and minor suppression were observed, but, uh, not so severe and well managed.

Kuan-Yu ChenHOST
好,呃,谢谢林医师的分享齁。那么接下来呢,呃,我们就请苏医师来跟大家分享,呃,关于,呃,rare oncogenic driver mutation,在这次,呃,WCLC 2026的内容。苏医师请。
Po-Lan SuGUEST
好,谢谢。那接下来就我,由我来为大家分享,就是关于 rare oncogenic driver alteration 在今年 WCLC 的发表。那这一次的发表主要都是在,呃,今天早上的 plenary session 的所有的那个报告这样子。那第一个部分我们,呃,我大概会主要分成三个部分。第一个部分是 EGFR exon 20 insertion,这部分有两个,就是报告。那另外还有 ROS1 的,就是,呃,fusion,然后以及 HER2 的那个 mutation,呃,各一个报告这样子。那我们就先从,呃,EGFR exon 20 insertion 这个 population 开始。那第一个是 PL03,那点零三的这个,呃,的报告,那它是 PAPIRON 的 study。PAPIRON 其实大家已经非常熟悉,它是一个,呃,phase three randomized study,那它收案是 treatment-naïve,uh, advanced stage non-small cell lung cancer,那同时它带有 EGFR exon 20 insertion 的病患。那它主要呢是去比较合并 nivolumab 和 platinum double chemotherapy 的一个疗效,然后去跟 chemotherapy alone 做比较。那之前的话,其实它已经有发表过它的 primary endpoint 的 analysis,那就是 progression-free survival,那有达到八点三个月,而且显著比,呃,对照组还要来得好。那今年的 WCLC 发表呢,其实就是做 overall survival,就总存活期的一个分析。那它的那个总存活期的分析的部分在,呃,treatment arm,就是 nivolumab 合并 platinum double chemotherapy 的部分,它的 median overall survival 是三十四点三个月,那相对于对照组 chemotherapy alone 呢是二十九,二十七点九个月,但是有比较长,但是 hazard ratio 呢是只有零点八七,那 P 值呢是零点三零七,没有显著吼。那这个没有显著,有一部分可能是因为它 study design 的关系,因为在 chemotherapy arm,它产生 disease progression 的时候,它是可以 crossover 到,呃,去使用 nivolumab monotherapy。那根据他们 trial 里面的统计,大概在一百二十八个有 disease progression 的 case 呢,其实还有九十七个都有接受到 nivolumab,nivolumab 的那个后续治疗。那在,呃,更进一步去看说他们这两个 arm 不同的 subsequent tre-treatment 的话呢,在 treatment arm,就是 combine nivolumab 跟 platinum double chemotherapy 这个 group,它其实有一半左右的病人,呃,有接受到 subsequent,呃,EGFR targeted therapy。但是相对的 chemotherapy arm 的话呢,除了刚刚说的有七十六 percent 是接受到 nivolumab 以外,另外还有大约,呃,十几 percent 的病人呢是接受到其他的 EGFR targeted therapy,所以它的比例到八成多。所以这部分呢有不,有-有可能会影响到它的就是 overall survival 的结果。那所以他们在这个 study 里面,他们有去做了一个,就是,呃,IPCW 的一个校正,那它当然就是,在,呃,有 crossover 的时候呢他就停止追踪,然后对于相类似的病人呢他会增加他的权重的一个校正方式,那就发现说他的 hazard ratio 可以降到零点五七,那 nom-nominally 的话呢是有显著这样子吼。那当然这是一个支持性的证据而已,它就没办法当成一个主证据。那在那个 safety 的部分呢,呃,目前是没有 new signal,它的数字上看起来在 EGFR inhibition associated 的 side effect,像 paraneoplastic rash 或是一些 dermatitis 的部分,数字比例上算偏高。啊不过这个 study 它开--起始的时候呢是还没有 subcu 的 form,然后它也没有,就是,呃,其他就 side effect management 的一些 study,所以这个是等于是在这些 study 之前的,所以它那个数字上其实是 align with previous 的 data。那所以目前是没有 new signal。那所以在这样子的一个,呃,报告过后呢,其实它是这样的一个 OS 的 numerical 的 benefit,其实它也是 support 它可以作为 first-line treatment 的一个证据这样子。那与之相类似的一个就是收案族群吼,那我们就进到下一个,就是 PL03.04 的这一个,呃,口头报告。那它的,呃,study 呢是 RESILIENT-3,这个 Phase 3 的 randomized study。那它同样是收案 treatment-naïve advanced stage 的 non-small cell lung cancer,那一样是带有 EGFR exon 20 insertion 的病患。那它比较的话呢,就是另外一种治疗组合,它是 ziprasidone,然后合-合并 platinum double 的 chemotherapy。那对照组一样是 chemotherapy alone。那 ziprasidone 呢,其实它,呃,过去我们比较知道的名字叫做 CL-CLN081啊,那它之前已经在 Phase 1、2 的 RESILIENT-1 study 呢,其实已经有一些 pretreated population 的一个发表,那它当时的 response rate 大概就是40%左右。那所以今年的 ASCO 的大会发表呢,主要就是去看它把它推到第一线,然后跟 chemotherapy 合并,那是不是可以比传统的 chemotherapy 来得-来啊-还要来得好。那今年发表的 primary endpoint 呢,是 primary endpoint 的分析,那是 progression-free survival。那在他们,呃,就是 combination 的这一组呢,它的 progression-free survival 可以到14.5个月。那相较于 control arm 的 chemotherapy alone 呢是只有8.5个月,那 hazard ratio 是可以到0.5,那 P值也有显著。所以经由这样子一个 study 之后呢,它也是成为第-- 另外一个可以使用的第一个一线选择。那它的 response rate 呢在 treatment arm 呢是可以到65%,那相对于 control 是40%,也是显著的比较高。那在 overall survival 的部分呢,目前,呃,还是 immature。那它那个在两个 arm 呢都是,呃,目前都还没有 reach median,那 P-value 呢也是没有显著这样子。那目前因为它的 study design 呢跟刚刚的 Papillon 有点类似,就是你在 chemotherapy 的 control arm decease-- 产生 decease progression 的时候呢,它一样可以去,呃,使用到 ziprasidone。所以也许它后面会跟 Papillon 的故事有点类似,就是它的 OS 也是只有 numerically 的 benefit 这样子而已。呃,那不过这大概,呃,还是不影响它,因为它 PFS 已经,呃,就是它的 primary point 已经达标,所以它还是可以成为一个很好的第一线选择。那在 safety 的部分,呃,就比较,呃,多一点问题这样子,它的那个 Grade 3 的 adverse event 呢会到,呃,80.7%。那它的那个就是 AE lead to treatment interruption 呢,其实,呃,也会到那个大概70几percent吼,那相较于 control arm 呢其实没有那么高。那其实比较值得注意的是说,它如果它去看 AE leading to treatment i-interruption 或是 dose reduction 的时候,其实是有分药物去看的,然后它是发现说 chemotherapy 的,就是影响,其实 the side-- 造成的 side effect 呢在 control arm 是比较高,所以有点在暗示说 ziprasidone 可能会增加 chemotherapy 的一个 side effect 这样子。那当然因为这样子的一个,呃,想法,因为 chemotherapy 当然我们在前面四个 cycle 有 platinum 的做一个 partner,所以它的那个 side effect 比较强,所以它后续也做了另外一个就是分析,就是说你在前四个 cycle 的 side effect 和后四个 cycle 的 side effect,其实它比例上是有一点差距的,前四个 cycle 的 side effect 会比较强,chemotherapy related 的 side effect 会比较强,那后四个 cycle,四个 cycle 以后呢就比较没有那么严重这样子,所以大概前面四个 cycle 的 AE management 就变成是一个比较关键的部分。那所以在这样子一个报告过后呢,那 RESILENT lung-- 呃,RESILENT-3 的这个 study,它也就把另外一个治疗组合 ziprasidone combine with platinum double chemotherapy 呢也推成一个第一线可以使用的治疗,那它有很好的那个 median PFS 的 benefit,然后也有 response 的 benefit。那我们未来呢大概比较需要注意的就是 AE management 部分,然后以及,呃,未来还-- 的它的那个 OS 的一个 data 在,呃,我们可以再等待它的发表。那以上大概就是两个,呃,EGFR exon 20 insertion 的部分,那接下来我们就进到,呃,HER2 mutation 的部分吼。那 HER2 mutation 今年 ASCO 大会发表是 dest-destiny-lung-04,那它也是一个 Phase 3 的 randomized study。那它收案呢是 treatment-naïve advanced stage non-small cell lung cancer,那而且带有,一,呃,HER2的 exon 19 或 exon 20 的 mutation。那它试验的比较就是 treatment arm,就是 trastuzumab deruxtecan,那简称 T-DSD 的一个 monotherapy。那它的 control arm 呢是 first-line 的 chemo-immunotherapy,那它的那个,呃,immunotherapy 的 partner 是 pembrolizumab。那 primary endpoint,primary endpoint 一样是 progression-free survival。那这一次的话呢,那个他们的,呃,在 treatment arm 的 primary,呃,for-- 不好意思,treatment arm 的那个 progression-free survival 是可以到14.3个月,那在那个,呃,就是 control arm 的是只有8.3个月,那,呃,是也是明显有显著,那 hazard ratio 是0.63。那所以以这样子一个 rich primary endpoint,它是,它等于是第一个 Phase 3 的 study 去证实 HER2-directed therapy 可以比,呃,我们一般 standard of care 的 treatment 还要来得好的的第一个 Phase 3 的临床试验,所以这算是一个非常重要的一个进步。 那目前 overall survival 就没有,呃,太好的一个 benefit,它的那个 treatment on 的 overall survival 是二十九点三个月,但是 control 是三十三点一个月,其实数字上还比较差一点。那当然统计学上是没有差别这样子啊。那会去——再回过头来看说会有这样子一个差异,可能还是跟它 subsequent therapy 会有一些影响。在 treatment on 的部分,第二线的治疗呢,其实只有少于一半的病人他是接受到 HER2-directed therapy,但是相对的在,呃,control 的 group 呢,它大概九十 percent 的病人都会接受到 HER2-directed therapy, either 是 ADC 或是 TKI,所以这可能也是会影响到它 overall survival 结果的其中一个原因。那AE的部分呢,是没有太多的,没有什么 new signal,那原则上大家最在意的还是 intersti-interstitial lung disease,那大部分的interstiti-interstitial lung disease 呢都是 grade one、two,而且会经过 management 之后都可以 resolve。那真的到 grade three 的话,大概是在两 percent 左右,那不过这个数字大概就跟过去报告的是差不多,所以这个还是大家非——在治疗上非常需要注意的,很小心的部分这样子。那所以这个,呃,这个 study 的话呢,我们简单做个总结,就是它其实是第一个 phase three 去,呃,指出 HER2-directed therapy 会比 standard of care 还要来得好的一个临床试验这样子。那,呃,未来在其他的那个 HER2-TKI 也会慢慢地会有,呃,那个 first-line 的临床试验出现,那我们可以再相互比较它们之间的一个结果。那最后呢,就是,呃,进到 ROS1 fusion 这一块,那这要分享的是那个 AROS1 的 study,那它是一个,呃, phase one、two 的 study,那使用的药物是 Lenvatinib,那过去比较大家比较熟悉的名字是 NBL520。那之前的话,其实它陆陆续续已经有非常多的发表,那包含说在,呃,有 G2032R,然后又没有使用过 Repotrectinib 的族群,response rate 呢是可以到六十五 percent,那-那如果说是有使用过 Repotrectinib 或是 Telotrectinib 这些的族群的话,response rate 大概是四十一到四十七 percent。那目前的今天的那个想要 focus 的是 TKI naive 的族群,那过去其实也有类似的发表过,那不过当时的人数比较少,所以今年是一个追踪的发表。那这个,它这个 treatment naive,应该说不能说是 treatment naive,应该是说是 TKI naive,因为它其实是 allow,呃,chemotherapy pre-treated 的 case。那它这个是在这个 study 里面的 phase two 的其中一个 cohort,那是,呃,ROS1 TKI naive 的一个 cohort,那总共收录的就是九十四个病人,那它的 response rate 呢就非常 promising,可以到九十四 percent,而且十二个月的 progression free survival 的 rate 呢是九十 percent。那像我们可以看看之前的像 Telotrectinib 或是 Repotrectinib,其实它的我们认为很 promising 的 ROS1 TKI 其实都有很类似的一个表现,所以它这个 response rate 是非常的好。那再来的话是 intracranial response 的部分,因为其实在 driver gene 的部分,我们都很在意它的 CNS activity,那它目前是只有十个有那个 brain mets 的病人,那不过这十个呢都是有 intracranial 的-的 response,所以它是100%。那当然也-也不是只有它有这么好的 benefit,像 Repotrectinib 跟 Telotrectinib,它的 response rate 呢也是都可以到八成以上,所以这几个 next generation 的 ROS1 TKI 都是有非常好的表现,在第一线,不管是 systemic 还是 intracranial 都有非常好的表现。那这-这个,这几个 TKI 可能比较大的差异会是在,呃,AE 的 profile 的部分,那 Lenvatinib 这个药物,它的 AE 的 profile 可能相对比较 tolerable,它比较多的 AE 是在 edema,呃,weight gain 啊,然后还有像,呃,比较 mild 的 hepatitis 或 dysgeusia,dysgeusia 这一块。那不过像 Telotrectinib 或 Repotrectinib,它可能就会比较多这些像那个更强的 hepatitis,然后还有一些 cognitive impairment 的部分。所以未来如果这些药都 available 的话,就是这个药也许是在 AE profile 上是一个比较 friendly 的选择这样子。那所以今——这个,这一次借由 AROS1 的这个,呃,single arm 的 study,那我们就又多了一个 Lenvatinib 可以——在第一线是一个很好的治疗选择,那也有一个比较好的一个 AE profile。那以上大概就是我今天对于 rare oncogene driver alteration 的一个,呃,简介,谢谢。
Kuan-Yu ChenHOST
好,谢谢苏医师的分享。那么接下来呢,我们请廖医师跟大家分享 ADC 和小细胞肺癌的内容。廖医师请。
Po-Lan SuGUEST
大家好,呃,我是廖宾之医师。那接下来我会分享今年比较重要的,尤其是针对小细胞肺癌的临床研究。那我想今年应该是唯一,呃,不知道是唯一,但是至少目前看起来同步发表在 New England Journal 的,大概就是这一篇小细胞肺癌的 ADC 的临床试验。那这篇是由,呃,中国张力教授所报告的,他们是用一个 ADC 叫,他们叫 TaM-Pally,那它是一个 B7-H3 的一个 antibody drug conjugate,那对上这个 Topotecan 作为,呃,二线治疗的一个选项,那这是一个 phase three 在中国执行的临床试验。那这个 TaM-Pally 这个 ADC,[咳嗽]它所用的这个,呃,payload 一样是 topoiso—— [咳嗽] topo one 的 inhibitor,那它的 DAR 是到八。
Bin-Chi LiaoGUEST
。那这个看起来,呃,这样的 Top- Top1的,的药物呢,过去是没有,没有在其他地方看过,那 potency 是不是比较强,那不是-- 不得而知。那这是一个第三期的临床试验,那病人一比一被 random 到接受 tempalimer 跟这个 topotecan治疗。那这些人他之前都已经接受过 systemic chemotherapy,那同时有将近八成的病人都同时有接受标准的这个 immunotherapy PD-1或PD-L1,因为我们在知道在中国,其实除了,呃,这个 Atezol跟 nivolumab 可以用,其实还有一些来自中国的一些免疫治疗吼,可以作为治疗上的一些选项。那这个临床试验当然就是直接就是以 overall survival作为它的 primary endpoint。那让我比较印象深刻的是,这个 trial 只花了十一个月左右的时间,就,呃,纳入了四百五十几位病人,那 randomized 一比一去接受,呃,不同的治疗选项,这个是我们非常不能够想象的速度,呃,非常快速,在短时间之内就把,呃,适合的病人都让他纳入到临床试验,呃,我想这个是在执行临床试验里面非常了不起的一个成就。那这些病人里面,呃,我觉得比较特别的是,在亚洲,吼,执行的小细胞肺癌临床试验,都 smoking- smoker 的比例都会稍微,呃,呃,没有像国外执行得那么高。哦,这样在这个临床试验里面,有三十percent的病人,他是 never smoker,哦。那在国外,像之前 Talortamab的304,Delphi 304,那 non-smo- never smoker大概就占十percent。那所以这是在,呃,亚洲执行,呃,小细胞肺癌的临床试验,有时候会稍微不太一样的。那至于 chemotherapy-free interval,那在这个 trial 里面,有一半的病人是大于九十天,一半的病人是小于九十天。好,那这个在跟 Delphi 304的,的 population 其实差不多的。那最重要的一个 primary endpoint 就是 overall survival。我们可以看到这边的 overall survival是十三点三个月,那比上 topotecan的这个九点四个月。好,我想 hazard ratio零点四六,那这是一个非常,呃,清楚的一个成绩,告诉我们确实是有很明显的 overall survival的 benefit。那我这边还是给大家,呃,这个 Talortamab在二线的 study 的表现的 data,好,它也是十三点五个月 versus 这个八个月,在-在 Delphi 304的 control 是八个月。好,所以说其实这两个 study 在 over-- 虽然是不同的药,但我们不能直接这样比较吼,不过确实这个药的成绩确实是可以达到这个十三点三个月这样的 overall survival,吼,确实一个非常好的一个成绩。那在 subgroup analysis 里面呢,那不管之前的这个,呃,chemo-free interval 是大于九十天还是小于九十天,那或是这个 B7-H3的 expression,好像,呃,并没有对这个 overall survival 造成太大明显的一些影响。那 progression-free survival,那虽然不是它的 primary endpoint,不过我们也可以看到非常不错的成绩。PFS 在 tempalimer 这一组可以到七点四个月,那在 topotecan这边是大概是二点八个月,那 hazard ratio 也是有到零点二九。好,不过我们当然看重的还是 overall survival 这个杰出的表现。那我个人其实比较印象深刻的应该还是这个 objective response rate。我们知道在 Talortamab,在 Delphi 304二线的 study 里面,呃,objective response rate 大概是三十五percent。那在-在这边的话,这个 tempalimer 这个药,它 objective response rate 可以到五十九percent,将近六十percent的一个 response rate。以一个ADC来讲,这样当然是一个非常不错的一个成绩,那也让我们对于 ADC 的这个标准吼,会越设越高。好,刚刚这个苏医师有提到,这个,这个,这个,呃,trastuzumab deruxtecan 在第一线的表现也是有非常高的一个 response rate,吼,所以我们对 ADC 的这个期待当然是会比标把,甚至比化疗都还要高非常多。那在 topotecan的话,这边的 response rate 大概是九点七吼。那不过 topotecan 这边的 response rate 跟在 Delphi 304的 chemotherapy arm 的二十percent的 response rate 好像就有点稍微不太一样。不过我们不要忘记 Delphi 304,其实它的 chemotherapy 是可以选mrubicine跟labrenectidine,虽然,呃,比例不多,好,但是这边还是给-- 提供给大家做一个参考。但我们不会直接拿这两个[轻笑] 临床试验去做直接比较吼,这样不太适合。好,不过确实一个将近六十percent的一个 ADC 的 response rate,在二线吼,确实是值得进一步的-- 大家进一步的关注。那更令人惊-惊艳的是它在 intracranial的 response rate 可以到三十二percent,三十二percent,然后,呃,呃,PFS,intracranial PFS是六点一个月。好,我想这也是针对我们有病人有 brain mets 一个非常好的一个 data。那 safety 方面,大家一定会担心 ADC Top1的常见的 ILD 的一个 side effect,那不过这边看起来整体在 grade 3以上的的这个,这个,这个,A-- treatment-related AE是四十六percent,那但是 topotecan当然这组是高达七十四percent。那刚刚有提到的这个 ILD 的这个比例,在这个 trial 是只有,只有五percent。好,所以这个 study 看起来在 ILD 的这个比例看起来是非常低的,好,所以这个也颠覆了我们过往对于 Top1的 ADC 的一些想象。 好,那接下来要介绍的一个是同场佳应,那一样是 B7-H3 的一个,的一个 ADC 的 study。那这个是 Phase III 的 Artemis study,那跟刚刚的这一个 Tyson study 非常像,它是用这个 Risвотamtaag,resiten,非常难念的一个药物,不过它一样是一个 B7-H3 的一个 ADC。那它的 DAR 是四,那用的是,呃,一样是 human IgG1 的一个 antibody,那再加上一个,呃,这个比较不一样的 Top1 的一个 inhibitor。那试验的设计跟刚刚的 Tyson study 非常像,病人一样是一比一被 random 到接受 ADC,那跟 Topotecan 的一个治疗。那 primary endpoint 看的一样是 overall survival。那在这个 study 里面一样,never smoker 也将占了将近三成的比例,感觉非常高,不知道有没有一些病人其实有一些 driver mutation,这个就不得而知。那比较不一样的是,这个临床试验里面,它 chemotherapy free interval 大于九十天的比例是稍微比较高的,有超过六成的病人是-是这样的病人,也许这样的病人也许对 chemotherapy 效果会比较好。好,不过跟刚刚前面一个 study 是百分之五十的大于九十天的 chemotherapy free interval,那会稍微有点不太一样。那不过瑕不掩瑜,我想 overall survival 的 primary endpoint,这边可以看到在 study arm 它的 overall survival,median 的 overall survival 是十八点五个月,那跟 Topotecan 的十个月来比较,hazard ratio 是零点四六。那 Topotecan 这边的表现看起来都比在这个 Delphi 304 要好。那我想现在目前小细胞的治疗已经不是过往的都没有什么药可以选择,现在的小细胞肺癌其实治疗选择非常多。其实我个人非常有兴趣的是,这些病人在接受完 study arm 或是 control 的治疗之后,到底接受了什么样的 subsequent line 的 treatment。以前我们在小细胞肺癌几乎不会去讨论这样的事情,不过现在在治疗选项越来越多的状况之下,我想后续的治疗的,我想大家应该可以,也-也许可以在 NEJM 的 paper 可以看得到,那我想后续应该会有更多的资料 release 出来。那在这个 safety 方面的话,这个药看起来,呃,我们先讲 objective response rate,一样成绩非常好,五十八percent 的 objective response rate,那我想跟刚刚前面的一个 Tempali 其实是不相上下。那不过在 safety 方面这边就是会有一些 concern,那一样大于 grade 3 的这个 toxicity,大概会有百分之六十病人会去遇到。那不过比较麻烦的是 IOD 的比例看起来是高达十一点七percent,那其中大于 grade 3 的有到三点九percent,所以跟刚刚前面一个药比起来,这个药的 IOD 的比例明显是增加。那其他一些 hematological 方面的 toxicity,我想大概就是这类 ADC 常见的一个问题。我想这两个 study 摆在一起是非常的适合,那其中有一篇还直接就上了 NEJM,那所以我想在未来的话,应该这些治疗的选项都会慢慢进入到我们的临床。那第一线,但是大家也别忘了,其实在前几天才发表这个 Delphi 305,那第一线的这一个 talatinib 的 combination 看起来是一个 positive result,所以这个未来 data 到底第一线要怎么样去使用,第二线要怎么选择,我想在武器越来越多,资料越来越多状况之下,我们这个小细胞肺癌的治疗应该可以让,我觉得病人这个 survival 站上一年,甚至超过一年以上,我觉得都是看起来应该是非常容易的事情,所以未来这个病人的 survival 大概也不是以前那种六到八个月病人就-就-就-就-就-就没有了,所以我想未来的治疗一定是非常的精彩。那接下来我们还要再加,呃,讲一个 talatinib,今年他在,呃,WCLC 有报告一个所谓的 expanded dose,那他的做法就是,他想要回答的问题说,这个 ex-extended interval dosing,也就是说我们一般都是 day 1 给1 mg,然后 day 8,然后给10 mg,那他直接 day 1 就是1 mg,day 8 就直接跳20,那有一组是直接跳30,然后,呃,C2 day 1 也一样是10,然后一组20,一组30,那只有到了在第三个 cycle 之后,原本给20的那一组才是延长到 Q3 week 给药,那原本给30的那一组就是变成 Q4 week 给药。那这样似乎是 extended 他的 interval,但是增加他的 dosing。那看起来这样的做法好像,呃,ORR、PFS 好像没有差得太多,那但是 PK profile 看起来这个药物的浓度当然就提高,相对应的一些这个 toxicity 看起来也是相对增加。哦,所以,呃,这个未来到底这个 talatinib 给法会不会因为这样的 study 而有所改变,我个人看法应该是没有,不过这还有待后续的研究,那陆续去看一下到底要怎么样给,因为两个礼拜就叫病人回来打一次药,确实也是有点辛苦,虽然病人有些如果还是,在台湾应该是还蛮-蛮愿意两个,但是有没有办法延长到比较久的时间,那又是另外一个课题。好,那现在我们就要离开小细胞肺癌,那我会... 好,接下来我们就离开小细胞肺癌,那我在非小细胞肺癌,我这边会讲一个 negative study,是 Evoke03,也就是 Keynote046 这样的一个 study。它是在 PD-L1 大于五十percent 的病人,那他想要回答的问题是,这样的病人如果是 单独使用pembrolizumab跟pembrolizumab如果加上sacituzumab govitecan这样一个ADC,会不会有比较好的结果。好,那病人是一比一被分到两组,那他的primary endpoint是PFS跟OS。那不过因为Alpha spending的-的-的-的结果,我们这边就直接看一下他的最后的统计分析。好,在SG再加上pembrolizumab这一组,他的PFS是十一个月,那versus pembro alone的七点七个月,那hazard ratio是零点八一,那p,p-value虽然是零点零二五二,但是因为Alpha spending的状况,所以这个其实是并,统计上并没有显著的一个差-差异。那另外overall survival看起来在这个study也没有太显著的差异。那我觉得比较,呃,有趣,但这个,这个discussion我觉得他的讨论其实非常有趣,就是在PD-L1大于fifty percent这样的病人,pembro的monotherapy看起来已经是奠定它完全不可动摇的地位了。不管你加上什么,像我们在KEYNOTE五九八加上atezolizumab,在LIB-007加上lenvatinib,在Keyfive甚至加了tigit,不管怎么加都没有办法动摇这个mo-monotherapy这一个角色,所以未来我们可能-- 那再加上这一个study,未来我们可能必须要思考在PD-L1 more than fifty percent,那病人是有考虑做pembro monotherapy,到底要怎么样去做combination才是比较好,才能真的帮助到这个pembrolizumab的效果,我想这个是未来我们必须要考虑的一个课题。我想今年的data其实非常多,那在这边就简单挑一些比较重要的,而且比较大型的跟大家分享,那以上跟大家报告。
Kuan-Yu ChenHOST
好,呃,谢谢廖医师喔。那么,呃,最后呢,呃,我们请三位哦,各用一分钟来做个简单的总结,我们从,呃,林医师开始。
Mong-Wei LinGUEST
好,呃,谢谢大家吼。就是我最后用一分钟把今年world lung跟胸腔外科最相关的讯息然后浓缩成三点哦。第一个当然就是early stage lung cancer的surgery还是在持续地deescalate吼,那但是今年哦,大概还是有一些peroperative outcome吼,所以真正能不能少切,其实还是要看这些今-- 这一两年开始的randomized trial的long-term outcome。第二个就是少切以后oncological outcome quality是更重要了哦,那要值得记住的数字就包括小于两公分的survivable的margin,大概是11mm以-以上是OK的了吼。那adequate的lymph node dissection至少要三个N1加一个N2。那第三个部分就是resectable的non-small cell lung cancer正进入一个biomarker driven的peroperative的era了吼,那包括MDT的BRIDGE哦,显示那个borderline的resectable的病人吼,接受peroperative的diva以后,其实有六成最后是可以接受手术了。那今年跟外科最相关的就是ADURO八年的结果要跟大家remind一下,就是five,呃,eight year的overall survival是七九versus六十四percent了吼,所以这个是一个相当不错的吼。不过也是IMpower030是negative的trial吼,也提醒我们,其实漂亮的PCR其实不一定等于EFS吼。所以最后做个总结,就是precision surgery哦,其实就是要选对病人,选对时间,还有范围了,然后把手术放在正确的multimodality的strate-strate-strategy里面,哦,谢谢大家。

Erica Bello RodriguezGUEST
So in that situation, the biomarker isn't just giving us additional molecular information, it's helping us understand why the cancer has changed and potentially what we can do differently.
Erica Bello RodriguezGUEST
And then I think about HER2 testing and the evolution of drugs like Trastuzumab Deruxtecan or Enhertu.
Erica Bello RodriguezGUEST
I think this is a really great example of how our understanding our biomarkers continue to evolve.
Erica Bello RodriguezGUEST
I'm thinking about a patient with metastatic breast cancer who has progressed through several lines of therapy.
Erica Bello RodriguezGUEST
Historically, we might have simply categorized that tumor as HER2 negative.
Erica Bello RodriguezGUEST
But with more sensitive testing, we can now identify patients whose tumors have lower levels of HER2 expression, such as HER2-low disease, and that information can potentially open the door to treatment with Trastuzumab Deruxtecan So we're not always looking at biomarkers as simply positive or negative anymore.
Erica Bello RodriguezGUEST
Sometimes the level of expression matters.
Erica Bello RodriguezGUEST
Another example would be a patient with metastatic gastric cancer who has progressed after standard therapy.

Erika P. HamiltonGUEST
How HER2CLIM05 fits in is a little bit more complicated a question in 2026.
Erika P. HamiltonGUEST
Certainly, you know, as the original maintenance studies were designed, whether we're talking about HER2CLIM05 or PATINA, both of these maintenance strategies were prior to us seeing results of DB09, uh, the trial that approved, uh, trastuzumab deruxtecan in combination with pertuzumab.
Erika P. HamiltonGUEST
So both of these trials looked at induction THP.
Erika P. HamiltonGUEST
So the PATINA regimen is approved only for the subset of patients with ER-positive disease, and I think that regimen will be used a lot for patients that have ER-positive disease.
Erika P. HamiltonGUEST
HER2CLIM05, on the other hand, is still an option for patients with ER-positive disease that I think will be used very heavily for patients that have ER-negative disease, again, because palbociclib is not an option for those patients.
Erika P. HamiltonGUEST
I think the question comes in around DB09 because in that trial, patients received trastuzumab deruxtecan in combination with pertuzumab, and that trial did not allow for any maintenance regimen.
Erika P. HamiltonGUEST
Now, despite that, in breast oncology, we move at a fast pace, and sometimes we have to go a little bit off the reservation because we move at a fast pace, and we don't really have clinical trial data, and we have to kind of integrate things without good randomized data.
Erika P. HamiltonGUEST
I think that there's still gonna be a high desire for patients for a maintenance regimen, even though that wasn't incorporated in Destiny BREAST09.

Monty PalHOST
First, we're gonna talk about frontline HER2 positive care.
Monty PalHOST
And Sarah, the Destiny-Breast09 data show that combining T-DXd with pertuzumab nearly doubled progression-free survival compared to our old standard THP.
Monty PalHOST
But many clinicians, they're looking closely at T-DXd monotherapy.
Monty PalHOST
In your practice, how do you decide between doublet of T-DXd plus pertuzumab versus T-DXd alone? I mean, are there certain patients, maybe those with de novo versus recurrent disease, where you still prefer monotherapy?
Sara TolaneyGUEST
Yeah, no, it's a really, a good question, a very interesting one.
Sara TolaneyGUEST
I think one of the challenges that we have when interpreting the Destiny-Breast09 data is that it did look at doublet therapy, so as you point out, it looks at T-DXd and pertuzumab.
Sara TolaneyGUEST
It also had an arm that looked at T-DXd alone and compared each of those arms to THP.
Sara TolaneyGUEST
But we only actually have seen data for the combination of T-DXd and pertuzumab compared to THP because at the time of the interim analysis for the trial, only the combination arm actually hit statistical significance, and the T-DXd monotherapy arm actually did not hit statistical significance at the time of the interim.

ChrisGUEST
Um, and that will be, um, some of the next data along with, um, the tumor PK, um, that we have, uh, that we have guided will be, uh, late this year.
ChrisGUEST
And so last data figure that we're gonna look at here, um, we compared the known, uh, PK of the release of deruxtecan from Enhertu, and this is essentially using AI to recreate, um, these data sets from, um, the published data, uh, with Enhertu and its release of deruxtecan, versus what do we see with, um, the release of exetican from AVA-六一零三.
ChrisGUEST
Now we're looking at, um, the first three dose levels, um, for, for each of these.
ChrisGUEST
And the, the message here is that we're seeing about, you know, estimates three times lower release in the plasma of the payload than was seen with equivalent, um, doses of Enhertu.
ChrisGUEST
Why is that important? Well, you can see, um, our exposure, just as we saw in the animals, the exposure in the bloodstream disappears, um, pretty quickly with those first three dose levels of, um, AVA-六一零三, as opposed to-- And, and in PK figures like this, when you stop, um, uh, when you, you, you stop the lines, that was when you stopped detecting it above the lower limit of detection, which is depicted there at point one nanograms per mil.
ChrisGUEST
And you can see at dose level two, uh, which is in, um, the, the very light green, as well as dose level three in the rusty color of exetican, or I'm sorry, of deruxtecan, released from Enhertu, we still detect that out, uh, multiple, uh, days later.
ChrisGUEST
Now, low levels, but even those low levels, um, in the, in the plasma can create, um, some of those, uh, toxicities.
ChrisGUEST
So we are thrilled, um, with how AVA-六一零三 is behaving in the clinic thus far.

Laura OwensGUEST
But every, every day w- I think I hold on to hope that the next great change is just around the corner.
Laura OwensGUEST
And with the ADC drugs that we've seen, that we're seeing trialed in a lot of sarcomas, we have had really great luck in DSRCT with a drug called Enhertu, which is approved in breast cancers.
Laura OwensGUEST
So I think that there are some, there's a lot of hope for the, that in the future, some of these new drugs that are coming out and being tested and approved in larger populations will be able to be applied and useful in more rare cancer populations like DSRCT.
Mark LevineHOST
Well, these, you know, this is important progress.

Courtney BensonGUEST
So I'm actually on the border between the two.
Courtney BensonGUEST
Um, so that's why I'm getting Enhertu.
Courtney BensonGUEST
So I had Red Devil, Taxol, and now I'm on Enhertu, which is what they gave metastatic breast cancer patients.
Courtney BensonGUEST
But it's now been released for mostly for triple positive, um, cancer patients who are not metastatic.
Courtney BensonGUEST
It has a signal that goes directly to the cancer, so it doesn't destroy your immune system.
31 MINS LATER
Courtney BensonGUEST
I've had 28 rounds of radiation.
DallasHOST
Okay.
Courtney BensonGUEST
So I did the radiation while getting Enhertu chemo.

Richard LeeGUEST
Yeah.
Richard LeeGUEST
A-a-and so that you summed it up very well, Tom, in, in that a drug called, um, Enhertu or trastuzumab deruxtecan, um, it, you know, it got its start in metastatic HER2 positive, uh, breast cancer kind of after other things didn't work anymore, right? And when it was shown to be successful in that setting, it's kind of moved up and up and up and up to earlier and earlier treatments.
Richard LeeGUEST
So now we actually have, um, Enhertu or trastuzumab deruxtecan being used in the neoadjuvant setting.
Richard LeeGUEST
So neoadjuvant setting is where we're giving treatment to a breast cancer before the patient's had surgery.
Richard LeeGUEST
And, you know, historically, that was always done, uh, you know, when you couldn't do an operation as your first treatment.
Richard LeeGUEST
And so now using Enhertu and, and oftentimes with other drugs, you can shrink tumors.
Richard LeeGUEST
And sometimes by the time you get through your surgery, you can have a scenario where when the surgeon removes that area of the breast or the whole breast, you can no longer find the cancer either in the breast or the lymph nodes.
Richard LeeGUEST
And that's, that's something we always get very excited about because we call that pathologic complete response.

CorrineHOST
If there is residual disease based on the KAPLAN trial, you do TDM1 for 14 cycles.
CorrineHOST
And then for high-risk residual disease, trastuzumab deruxtecan, T-DXd, is now an option based on the Destiny Breast 05 approved in May of this year.
CorrineHOST
And then if they're ERPR positive, you are also going to give endocrine therapy for five to 10 years.
CorrineHOST
Don't forget about monitoring for cardiotoxicity with serial echoes.
CorrineHOST
For HER2 positive, those under two centimeters that are node-negative, you can do surgery first, followed by taxol trastuzumab.
CorrineHOST
If they're more than two centimeters or node-positive, neoadjuvant TCHP.
CorrineHOST
For residual disease, our historical regimen has been TDM1 based on the KAPLAN trial, and now we also have T-DXd for high-risk residual disease.
SamHOST
Definitely.
16 more episodes mention Trastuzumab deruxtecan.
Create an account to see the whole feed, search across every transcript, and follow the entities you care about.